
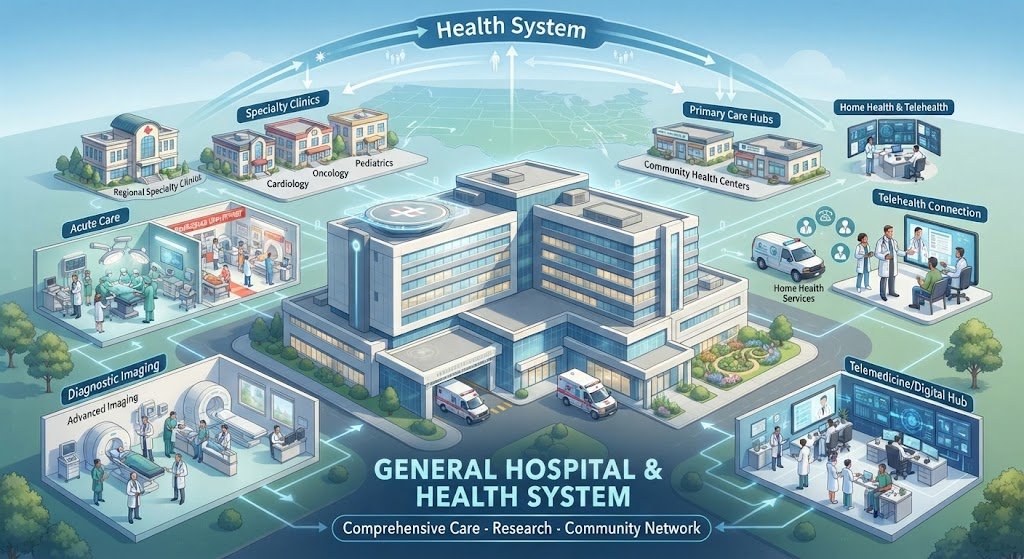
Artificial intelligence is moving from isolated hospital experiments toward a broader health-system operating layer. The strongest near-term opportunities are clinical documentation, emergency triage, patient deterioration detection, sepsis prediction, medical imaging, hospital admission forecasting, patient-flow optimization, readmission prediction, clinical decision support and administrative automation. Research increasingly shows that AI can improve prediction and reduce workload, but performance alone is not enough. General hospitals need prospective validation, workflow integration, human oversight, cybersecurity, equity monitoring and continuous post-deployment evaluation. The next generation of health systems will likely combine AI with electronic health records, medical devices, imaging, operational data and generative AI to create more proactive, connected and personalized care.
AI in General Hospitals: Current Trends & Future Predictions
General hospitals are among the most complex environments in healthcare. Emergency departments, intensive care units, operating rooms, laboratories, radiology departments, pharmacies, inpatient wards, outpatient clinics and administrative teams all operate within the same system.
Every department generates large amounts of information. Vital signs, laboratory results, medical images, physician notes, nursing documentation, medication records, appointments, bed availability and patient histories create a continuous stream of data.
Artificial intelligence can turn this data into predictions, summaries, alerts, recommendations and automated workflows. That makes general hospitals one of the largest potential environments for practical AI adoption.
The opportunity is also driven by pressure on health systems. WHO reported that global health spending reached US$9.8 trillion in 2021, equivalent to 10.3% of global GDP. Hospitals, ambulatory care providers and pharmacies accounted for most health spending, highlighting the scale of the systems that need to become more efficient.
AI therefore matters for two different reasons. It can support better clinical decisions, and it can help hospitals use limited staff, beds, equipment and time more efficiently.
Key Findings
- 81% of surveyed physicians reported using AI professionally in the AMA’s 2026 survey, more than double the 38% reported in 2023.
- A 2025 randomized trial of 238 physicians across 14 specialties found that one ambient AI scribe reduced time spent in notes by 9.5% compared with usual care.
- A separate randomized implementation trial involving 66 healthcare practitioners and 71,487 notes found that ambient AI reduced time spent on notes by about 0.36 hours per day.
- A 2025 prospective validation study of an AI deterioration model included 205,946 admissions in prospective validation and found AUROC of at least 0.80 across multiple subgroups.
- A prospective hospital study of 6,797 patients evaluated an AI algorithm for early sepsis prediction using real-world electronic medical record data.
- A 2025 systematic review of hospital admission prediction included 20 studies and reported AI model accuracy generally between 85% and 95%, although most studies were retrospective.
- A systematic review of machine learning for inpatient admission prediction found 31 studies, with seven demonstrating strong methodology and AUROC values between 0.81 and 0.93.
- A 2025 systematic review of AI-assisted cancer imaging included 34 studies. In the meta-analysis, AI-assisted clinicians achieved pooled sensitivity of 0.79 and specificity of 0.87 compared with 0.67 and 0.82 for clinicians without AI assistance.
- Recent emergency-department reviews show AI triage models can reach high retrospective AUC values, but prospective implementation evidence remains limited.
- The FDA’s AI-enabled medical device list now contains a rapidly expanding number of authorized AI devices, with radiology representing a large part of the current landscape.
Why General Hospitals Are Becoming AI Operating Environments
A hospital is not one workflow. It is a network of interconnected workflows.
A patient may enter through the emergency department, receive laboratory testing and imaging, move to an inpatient ward, receive medications, undergo a procedure, be discharged and later return for follow-up.
AI can potentially connect these stages.
Traditional Hospital Model
Patient → Department → Department → Department → Discharge
AI-Enabled Health System
Patient Data → AI Analysis → Clinical Decision Support → Workflow Automation → Continuous Monitoring → Outcome Feedback
This shift is important because the value of AI is often greater when multiple data sources are combined. A laboratory result alone may be useful. A laboratory result combined with vital signs, medication history, nursing notes and recent clinical changes can provide a much richer picture.
Research Analysis 1: Physician Adoption Is Moving Into the Mainstream
AI adoption is no longer limited to digital-health specialists.
The American Medical Association’s 2026 physician survey found that 81% of surveyed physicians reported using AI professionally. This was more than double the 38% reported in the AMA’s 2023 survey. The most common uses included summarizing medical research and standards of care, creating discharge instructions, documentation, chart summaries and other administrative tasks.
Original AMA research and survey report.
Physician AI Adoption
2023
38%
2026
81%
Key implication: Hospital AI is shifting from experimentation toward everyday professional use.
The most important lesson is that adoption begins where AI solves a visible problem. Doctors are more likely to use a tool that saves documentation time or summarizes complex information than one that asks them to completely change their clinical decision-making process.
Research Analysis 2: Ambient AI Can Reduce Documentation Burden
Clinical documentation is one of the clearest hospital AI opportunities because clinicians spend substantial time documenting care.
A 2025 randomized clinical trial at a large academic health system evaluated two ambient AI scribes. The study recruited 238 outpatient physicians across 14 specialties. One AI scribe, Nabla, reduced time spent in notes by 9.5% compared with the usual-care control group. Original PubMed study.
Another randomized pragmatic trial evaluated ambient AI among 66 healthcare practitioners across ambulatory clinics. During the study, 71,487 notes were authored and 27,092 were generated using ambient AI. AI use reduced time spent on notes by 0.36 hours per day and reduced work exhaustion/interpersonal disengagement by 0.44 points on the study scale. Original PubMed study.
Ambient AI Documentation Evidence
| Study | Scale | Key Result |
|---|---|---|
| Randomized AI scribe trial | 238 physicians | 9.5% reduction in note time with Nabla |
| Pragmatic randomized trial | 66 practitioners / 71,487 notes | 0.36 fewer hours/day spent on notes |
| 2025 observational pilot | 38 physicians/APPs | Burnout rate fell from 69% to 43% |
These studies do not prove that every AI scribe will create the same result. They do, however, demonstrate that documentation is one of the rare hospital AI areas where measurable workflow benefits are already appearing in real clinical environments.
Research Analysis 3: AI for Emergency Department Triage
Emergency departments are ideal environments for predictive AI because clinicians must make rapid decisions using incomplete information while patient volumes can change dramatically.
A 2026 systematic review analyzed eight retrospective or cross-sectional studies involving samples ranging from 2,000 to more than 2.6 million patients. XGBoost was repeatedly among the strongest-performing approaches, with AUC values between 0.76 and 0.96. NLP improved prediction when unstructured clinical data were added to structured information.
However, the review found no prospective implementation studies among the included evidence. Original PubMed research.
A separate 2025 systematic review of prospective studies identified seven eligible studies from 1,633 records. Reported triage prediction accuracy ranged from 80.5% to 99.1%, depending on the model and outcome. Original PubMed research.
AI Emergency Triage Evidence
| Evidence | Finding | Hospital Implication |
|---|---|---|
| 2026 systematic review | AUC 0.76–0.96 | Strong prediction potential |
| 2025 prospective review | Accuracy 80.5–99.1% | Evidence is moving into clinical settings |
| 2026 scoping review | 27 studies | Workflow integration remains a major gap |
The lesson for hospitals is simple: an AI triage model should not be evaluated only by AUC. A hospital should also measure waiting time, undertriage, overtriage, missed critical cases, clinician workload, equity and patient outcomes.
Research Analysis 4: AI for Clinical Deterioration
One of the most important hospital AI applications is identifying patients who are beginning to deteriorate before the situation becomes obvious.
Machine-learning early warning systems can analyze vital signs, laboratory results, demographics, medications and other clinical information continuously rather than waiting for a clinician to manually recognize a pattern.
A major 2025 multicenter study developed and prospectively validated eCARTv5. The development cohort contained 901,491 admissions, retrospective validation included 1,769,461 admissions and prospective validation included 205,946 admissions.
In retrospective validation, eCARTv5 achieved an AUROC of 0.834, compared with 0.775 for an earlier eCART model, 0.766 for NEWS and 0.704 for MEWS. Performance remained at AUROC 0.80 or higher across multiple demographics and clinical conditions during prospective validation. Original PubMed study.
Early Warning Model Comparison
| Model | Retrospective AUROC |
|---|---|
| eCARTv5 | 0.834 |
| eCARTv2 | 0.775 |
| NEWS | 0.766 |
| MEWS | 0.704 |
Another clinical evaluation at an academic medical center included 13,649 general internal medicine admissions and 8,470 admissions in comparison subspecialty units. The study evaluated a real-time machine-learning early warning system for deterioration and found a significant reduction in non-palliative in-hospital deaths during the intervention period in general internal medicine. Original CMAJ/PubMed study.
This is an important distinction. Predictive accuracy is one level of evidence. Demonstrating an association with actual clinical outcomes after implementation is a much more meaningful level.
Research Analysis 5: AI for Sepsis Prediction
Sepsis is another area where minutes can matter. Traditional screening approaches may rely on combinations of vital signs, laboratory values and clinical assessment. AI can continuously evaluate changing patterns across multiple variables.
A 2025 prospective observational study evaluated a deep-learning sepsis prediction system using real-world electronic medical record data from 6,797 hospitalized patients. The model was designed to predict sepsis and monitor patient conditions using hospital data. Original PubMed study.
Another 2025 study developed and prospectively implemented COMPOSER-LLM, an LLM-based extension designed to use information from unstructured clinical notes alongside structured EHR data for early sepsis prediction. Original Nature/PubMed study.
This is where generative AI and traditional predictive models may begin to converge. Structured models can analyze numerical data efficiently, while language models can extract contextual information from physician and nursing notes.
Potential AI Sepsis Workflow
Vital Signs + Labs + Medication Data + Nursing Notes + Physician Notes
↓
AI Risk Analysis
↓
Early Risk Signal
↓
Clinician Review
↓
Sepsis Protocol / Further Assessment
↓
Continuous Monitoring
Research Analysis 6: AI for Hospital Admission Prediction
Hospitals lose significant capacity when emergency departments, inpatient beds, operating rooms and discharge processes become disconnected.
AI can predict which emergency patients are likely to require admission before the final decision is made. This allows hospitals to prepare beds, staff and downstream services earlier.
A 2025 systematic review examined 20 studies published between 2019 and 2024. Most were retrospective, but AI models generally demonstrated accuracy between 85% and 95%, with Random Forest and neural networks outperforming classical statistical models in the included studies. NLP-based models using unstructured information also improved patient-flow and resource-allocation predictions. Original PubMed study.
A separate systematic review identified 700 articles and ultimately included 31 studies evaluating machine learning for predicting inpatient admissions from emergency-department triage data. Seven studies demonstrated particularly rigorous methodology, with AUROC values ranging from 0.81 to 0.93. Original PubMed study.
Hospital Admission Prediction
Reported accuracy range in 2025 systematic review
Approximately 85%–95%
Rigorous studies: AUROC range
0.81–0.93
The business value is potentially significant. Earlier admission forecasting can support bed management, staffing, imaging capacity, pharmacy preparation and discharge planning.
Research Analysis 7: AI for Patient Flow and Bed Management
Patient flow is a system-wide problem. A hospital can have enough total beds but still experience overcrowding if the wrong beds are available at the wrong time.
A 2025 scoping review examined 25 studies on eHealth and AI tools used to improve in-hospital patient flow. Forty percent of the studies were quasi-experimental, and 19 were conducted in the United States. The most common approach involved embedding digital or AI tools into existing electronic health records.
The review identified environmental and resource constraints as common implementation barriers, while social influence and organizational support were important facilitators. Original PubMed study.
This demonstrates a critical point: AI implementation is not only a technology problem. A highly accurate prediction model can fail if nurses do not trust alerts, managers cannot act on the information or the hospital does not have a process for responding to predictions.
Research Analysis 8: AI for Hospital Readmission Prediction
Readmissions create clinical and financial pressure for health systems. Predicting which patients are more likely to return can help hospitals target discharge planning and follow-up resources.
A 2025 systematic review of machine-learning approaches for general internal medicine readmission prediction examined nine U.S. studies covering conditions including heart failure, myocardial infarction, pneumonia and COPD. Artificial neural networks and Random Forest models generally outperformed traditional regression approaches, while NLP-based methods showed more limited success in the reviewed studies. Original PubMed study.
An earlier systematic review identified 77 hospital readmission prediction studies. Traditional regression remained dominant, while 18% of studies used machine-learning classification methods. Original PubMed research.
The opportunity is not simply to predict readmission. The real value comes when prediction changes care.
Prediction-to-Action Model
AI Identifies High-Risk Patient
↓
Discharge Team Review
↓
Medication / Follow-Up Check
↓
Earlier Outpatient Appointment
↓
Remote Monitoring
↓
Reduced Avoidable Return Risk
Research Analysis 9: AI-Assisted Medical Imaging
Medical imaging is one of the most mature areas of clinical AI because hospitals already produce enormous quantities of radiology images.
The FDA’s current AI-enabled medical device database shows a large and growing number of authorized AI-enabled products, with radiology representing a major portion of the list. Current examples include AI systems for CT, ultrasound, mammography, cardiovascular imaging, cancer imaging and other radiological applications. Original FDA database.
A 2025 systematic review and meta-analysis evaluated AI-assisted radiology assessment for cancer. Thirty-four studies were included and 23 entered the quantitative meta-analysis. The pooled sensitivity for clinicians without AI assistance was 0.67 and specificity was 0.82. With AI assistance, pooled sensitivity increased to 0.79 and specificity to 0.87.
However, 17 of the 34 studies had concerns regarding risk of bias. Original PubMed systematic review.
AI-Assisted Cancer Imaging
| Approach | Sensitivity | Specificity |
|---|---|---|
| Clinicians without AI | 0.67 | 0.82 |
| AI-assisted clinicians | 0.79 | 0.87 |
This is a strong example of the most useful hospital AI model: human plus AI rather than AI instead of human.
Research Analysis 10: AI for Length of Stay
Length of stay affects bed availability, staffing, hospital costs and patient flow. Predicting length of stay early can help hospital managers identify patients who may require additional resources.
A systematic review of hospital length-of-stay prediction methods examined studies using hospital data, different prediction algorithms and multiple validation approaches. The review found substantial variation in the quality of methods and highlighted the importance of validation design and the choice of performance metrics. Original PubMed systematic review.
The future opportunity is to combine length-of-stay prediction with operational decisions. Instead of simply saying that a patient is likely to stay seven days, an integrated system could identify why the stay may be extended and what intervention could potentially accelerate a safe discharge.
AI Across the General Hospital
| Hospital Department | AI Application | Potential Impact |
|---|---|---|
| Emergency Department | Triage, admission prediction, risk scoring | Faster prioritization and flow |
| ICU | Deterioration, mortality and monitoring | Earlier intervention |
| Radiology | Image analysis and prioritization | Diagnostic support |
| Cardiology | ECG and imaging analysis | Earlier detection and risk assessment |
| Pathology | Digital slide analysis | Diagnostic assistance |
| Pharmacy | Medication reconciliation and alerts | Medication safety |
| Nursing | Risk alerts and workload support | Earlier response |
| Administration | Scheduling and automation | Lower workload |
| Bed Management | Demand and admission forecasting | Higher capacity utilization |
Maximum AI Use Cases for General Hospitals
1. AI Clinical Documentation
Ambient AI can listen to clinical encounters and prepare draft notes, summaries and structured documentation for clinician review.
2. AI Patient Intake
Conversational systems can collect medical history, symptoms and administrative information before a consultation and transform it into structured data.
3. Emergency Triage
Machine-learning models can analyze symptoms, vital signs, arrival information and clinical text to support patient prioritization.
4. Clinical Deterioration Alerts
AI can continuously analyze inpatient data to identify patients whose risk of deterioration is increasing.
5. Sepsis Prediction
AI can combine laboratory results, vital signs and clinical notes to identify potential sepsis earlier.
6. Medical Imaging
Computer vision can support radiologists with detection, classification, segmentation, prioritization and quantitative measurements.
7. ECG and Cardiac AI
AI can analyze electrocardiograms and other cardiac signals to identify patterns associated with arrhythmia, cardiac dysfunction and other conditions.
8. Patient Flow Optimization
AI can predict admissions, discharges, bed demand and department congestion to improve hospital-wide flow.
9. Readmission Prediction
Machine-learning models can identify patients who may benefit from additional discharge planning and follow-up.
10. Length-of-Stay Prediction
AI can forecast likely length of stay and help hospitals identify operational bottlenecks.
11. Medication Safety
AI can support medication reconciliation, interaction detection and identification of unusual medication patterns.
12. Clinical Decision Support
AI can summarize patient information and surface relevant clinical evidence for professional review.
13. AI Patient Monitoring
Connected devices and predictive models can monitor patients continuously and generate risk alerts.
14. Discharge Planning
AI can identify missing discharge tasks, summarize medication changes and prepare patient-facing instructions for clinician approval.
15. Revenue Cycle Automation
Generative AI and NLP can support coding, documentation review, claims workflows and administrative communication.
16. Workforce Forecasting
Predictive analytics can forecast patient volumes and help managers plan staffing requirements.
17. Operating Room Optimization
AI can support scheduling, case duration prediction, cancellation forecasting and operating-room utilization.
18. Supply Chain Forecasting
Machine learning can predict demand for medications, equipment and consumables and help reduce shortages or excess inventory.
19. Infection Surveillance
AI can identify patterns across laboratory, patient and environmental data that may indicate infection clusters.
20. Hospital Knowledge Assistants
Generative AI can provide controlled access to hospital policies, clinical guidelines and internal knowledge bases.
General Hospital AI Capability Map
| Technology | Hospital Applications | Current Opportunity |
|---|---|---|
| Generative AI | Documentation, summaries, patient communication | Very High |
| Machine Learning | Risk prediction, readmission, patient flow | Very High |
| Computer Vision | Radiology, pathology, medical imaging | Very High |
| Natural Language Processing | Clinical notes and unstructured records | Very High |
| Predictive Analytics | Demand, staffing, beds and operations | High |
| Speech AI | Ambient documentation and voice interfaces | High |
| Workflow Automation | Administrative and operational workflows | Very High |
AI Hospital Architecture
Future AI Health System Architecture
EHR + Medical Imaging + Laboratory + Pharmacy + Monitoring Devices + Scheduling + Operational Data
↓
Healthcare Data & Integration Layer
↓
Machine Learning + Computer Vision + NLP + Generative AI + Predictive Analytics
↓
AI Decision & Automation Layer
Clinical Alerts + Documentation + Patient Flow + Risk Prediction + Patient Communication
↓
Human Clinical Oversight
Doctors + Nurses + Pharmacists + Radiologists + Administrators
↓
Continuous Monitoring & Quality Improvement
Legacy Hospital Modernization
Many established hospitals have multiple software systems that were introduced at different times. EHRs, PACS, laboratory systems, pharmacy systems, billing platforms, scheduling tools and patient portals may not communicate efficiently.
This creates one of the biggest barriers to AI adoption: data fragmentation.
Hospitals do not necessarily need to replace their entire technology stack. A more practical approach is to create an integration layer that connects existing systems and introduces AI capabilities gradually.
Legacy-to-AI Transformation
| Legacy Environment | AI Modernization |
|---|---|
| Disconnected EHR data | Integrated data layer |
| Manual documentation | Ambient AI documentation |
| Static alerts | Predictive risk alerts |
| Reactive bed management | Demand forecasting |
| Manual patient communication | AI-assisted communication |
| Department-level analytics | Enterprise health-system analytics |
Major Industry Trends
Trend 1: AI Is Moving From Pilot Projects to Health-System Infrastructure
Hospitals increasingly need AI systems that work across departments instead of isolated tools that solve one small problem.
Trend 2: Generative AI Is Expanding the User Base
Traditional predictive AI often required specialized clinical software. Generative AI creates interfaces that doctors, nurses, administrators and patients can use through natural language.
Trend 3: Ambient Documentation Will Be One of the Fastest Adoption Areas
Documentation AI addresses a clear operational problem and can create measurable time savings without requiring autonomous diagnosis.
Trend 4: Predictive AI Is Moving Earlier in the Patient Journey
Instead of waiting for deterioration, hospitals are increasingly interested in predicting risk before it becomes clinically obvious.
Trend 5: AI Will Connect Clinical and Operational Intelligence
The next generation of hospital AI will combine clinical data with operational data. Bed availability, staffing, patient risk and expected discharge can be analyzed together.
Trend 6: Medical Imaging AI Will Continue Expanding
The FDA’s continuously updated AI-enabled device database demonstrates how quickly AI is entering regulated medical devices, especially in radiology and imaging.
Original FDA AI-enabled device database.
Trend 7: Human-AI Collaboration Will Become the Dominant Model
Research increasingly shows value from AI-assisted clinicians rather than fully autonomous clinical systems. This approach combines algorithmic pattern recognition with professional judgment.
AI Safety and Governance for Health Systems
Large hospitals cannot treat AI like ordinary enterprise software. Clinical AI affects patient care, privacy, professional responsibility and potentially life-or-death decisions.
WHO’s guidance on AI in health identifies human autonomy, safety, transparency, accountability, equity and sustainability as core principles. WHO specifically states that humans should remain in control of healthcare systems and medical decisions. Original WHO guidance.
WHO’s later guidance on large multimodal models also addresses the growing use of generative AI systems that can process multiple types of information. Original WHO guidance.
| AI Risk | Hospital Protection |
|---|---|
| Incorrect prediction | Clinical validation and human review |
| Hallucinated information | Grounded AI and controlled knowledge sources |
| Bias | Subgroup validation and fairness monitoring |
| Privacy breach | Encryption, access controls and audit logs |
| Alert fatigue | Threshold optimization and workflow design |
| Model drift | Continuous post-deployment monitoring |
| Cybersecurity | Security testing and strict system access |
The Hospital AI Adoption Framework
Stage 1: Automate
Start with administrative workflows, documentation, scheduling, communication and routine information processing.
Stage 2: Assist
Introduce clinical summaries, imaging assistance, knowledge retrieval and clinician copilots.
Stage 3: Predict
Deploy validated models for deterioration, admission, readmission, sepsis and operational forecasting.
Stage 4: Integrate
Connect AI models across the EHR, imaging, laboratory, pharmacy, monitoring and operational systems.
Stage 5: Optimize
Use continuous analytics to improve patient flow, staffing, resource utilization and clinical outcomes.
Original Research Asset: Hospital AI Opportunity Matrix
| Use Case | Clinical Value | Implementation Difficulty | 2027–2030 Outlook |
|---|---|---|---|
| Ambient documentation | Very High | Medium | Mainstream |
| Medical imaging AI | Very High | High | Rapid growth |
| Deterioration prediction | Very High | Very High | Clinical expansion |
| Sepsis prediction | Very High | Very High | High-risk regulated growth |
| Patient flow | High | High | Strong growth |
| Readmission prediction | High | High | Strong growth |
| Hospital knowledge AI | High | Medium | Mainstream |
Future Predictions: 2027–2030
Prediction 1: Hospitals Will Build Enterprise AI Platforms
Instead of purchasing dozens of disconnected AI tools, large health systems will increasingly want enterprise platforms capable of managing multiple AI applications through common governance, security and data infrastructure.
Prediction 2: AI Will Become a Hospital Operating Layer
AI will increasingly sit between clinical data and operational decision-making. It will not only identify disease patterns but also help determine which resources should be prepared and when.
Prediction 3: Ambient Documentation Will Become Standard
The evidence around documentation burden is already stronger than many other healthcare AI applications. As integration improves, ambient documentation will likely become a normal feature of hospital and outpatient workflows.
Prediction 4: Predictive Hospitals Will Replace Reactive Hospitals
Today’s hospital often reacts to deterioration, overcrowding, staffing shortages and unexpected admissions. Future systems will increasingly forecast these events before they occur.
Prediction 5: AI Will Connect Clinical and Operational Data
The strongest systems will combine patient risk with bed availability, staffing, operating-room capacity, pharmacy demand and expected discharge dates.
Prediction 6: Medical Imaging AI Will Become More Multimodal
Radiology AI will increasingly combine images with clinical history, laboratory results and prior imaging instead of analyzing each image in isolation.
Prediction 7: Hospital Knowledge Assistants Will Become Common
Generative AI will increasingly provide controlled access to internal policies, clinical pathways, formularies, operational procedures and research evidence.
Prediction 8: Continuous AI Monitoring Will Become More Important
Hospitals will increasingly monitor AI systems after deployment for accuracy, bias, drift, false alerts and differences in performance between patient groups.
Prediction 9: AI Procurement Will Become More Evidence-Based
Hospital executives will increasingly demand prospective validation, external validation, safety data, interoperability and measurable workflow outcomes before approving large AI deployments.
Prediction 10: Human-AI Teams Will Become the Normal Model
The future hospital is unlikely to be fully automated. Instead, clinicians, administrators and AI systems will work together, with each handling the tasks it performs best.
Recommendations for Hospital Leaders
- Start with measurable problems. Choose areas such as documentation, patient flow, triage or discharge where the baseline problem can be quantified.
- Do not buy AI based only on accuracy claims. Ask for external validation, prospective evidence and real-world implementation results.
- Build the data foundation first. Poorly integrated data can undermine even strong AI models.
- Keep humans accountable. AI should support healthcare professionals rather than silently make high-risk decisions.
- Measure workflow impact. Track time saved, alert burden, adoption, patient outcomes and clinician satisfaction.
- Monitor equity. Evaluate model performance across demographic and clinical subgroups.
- Design for interoperability. AI should connect with existing EHR, PACS, laboratory, pharmacy and operational systems.
- Create an AI governance committee. Clinical, technical, legal, cybersecurity, ethics and patient-safety teams should participate.
- Monitor models continuously. Performance can change after deployment as patient populations and workflows change.
- Train the workforce. Doctors, nurses and administrators need practical training on AI limitations and responsible use.
What Healthcare Startups Can Build for General Hospitals
General hospitals create a much larger AI opportunity than a single clinical application. Startups can build solutions around individual departments or create platforms that connect multiple workflows.
| Startup Opportunity | Primary Buyer | Value Proposition |
|---|---|---|
| Ambient AI scribe | Clinical leadership | Reduce documentation workload |
| Hospital command center AI | Operations | Optimize beds and patient flow |
| Clinical deterioration AI | Patient safety / clinical leadership | Earlier intervention |
| Radiology AI | Radiology departments | Diagnostic assistance |
| AI discharge assistant | Care management | Improve discharge efficiency |
| Hospital knowledge assistant | Enterprise leadership | Fast access to trusted information |
| Predictive staffing | Operations / HR | Match workforce to demand |
AI Services Required for Hospital Transformation
Large hospital AI projects usually require several capabilities rather than a single model. Organizations may need AI development, AI integration, workflow automation, machine learning, computer vision, custom model development, data analytics and generative AI.
For healthcare organizations planning this type of modernization, relevant capabilities include AI development, AI integration, AI workflow automation, machine learning, computer vision development, custom AI model development, data analytics and AI insights and generative AI development.
Frequently Asked Questions
How is AI being used in general hospitals?
AI is being used for clinical documentation, medical imaging, emergency triage, patient deterioration prediction, sepsis detection, readmission prediction, patient flow, hospital admission forecasting, staffing, scheduling and clinical decision support.
What is the most mature hospital AI application?
Medical imaging is among the most mature regulated clinical AI areas, while ambient clinical documentation is one of the fastest-growing workflow applications. Both areas now have real-world evidence beyond simple laboratory demonstrations.
Can AI replace doctors in hospitals?
Current evidence does not support replacing doctors with AI. The strongest model is human-AI collaboration, where AI processes large amounts of data and identifies patterns while clinicians retain responsibility for diagnosis, treatment and high-risk decisions.
Can AI predict patient deterioration?
Yes. Multiple studies have demonstrated that machine-learning early warning systems can predict deterioration with strong discrimination. Some newer models have also undergone prospective multicenter validation. However, prediction must be connected to a reliable clinical response workflow.
Can AI predict hospital admissions?
Yes. Research shows that machine-learning models can predict which emergency-department patients are likely to require admission. This can help hospitals prepare beds, staff and downstream resources earlier.
What is the biggest barrier to hospital AI adoption?
The biggest barrier is often not model performance. Data integration, workflow design, clinician trust, interoperability, cybersecurity, governance and the ability to act on AI predictions can determine whether a technically strong system creates real value.
What should hospitals implement first?
Lower-risk, measurable workflows such as documentation, administrative automation, knowledge retrieval, patient communication and operational forecasting are strong starting points. Hospitals can then move toward higher-risk clinical prediction systems after establishing governance and validation processes.
Credible Research Sources
- WHO: Global Spending on Health: Coping With the Pandemic
- American Medical Association: More Than 80% of Physicians Use AI Professionally
- Ambient AI Scribes in Clinical Practice: A Randomized Trial
- Pragmatic Randomized Trial of Ambient AI to Improve Healthcare Practitioner Well-Being
- The Effect of Ambient Artificial Intelligence Notes on Provider Burnout
- Systematic Review of AI and Machine Learning Applications in Emergency Department Triage
- Systematic Review of Prospective AI Triage Studies
- AI-Assisted Triage in Emergency Departments: 2026 Scoping Review
- Multicenter Development and Prospective Validation of eCARTv5
- Clinical Evaluation of a Machine Learning Early Warning System
- Prospective Validation of an AI Algorithm for Sepsis Prediction
- Development and Prospective Implementation of an LLM-Based System for Early Sepsis Prediction
- AI for Hospital Admission Prediction and Flow Optimization: Systematic Review
- Machine Learning for Predicting Inpatient Admissions From Emergency Triage
- AI-Based Tools to Optimize In-Hospital Patient Flow
- Machine Learning for Hospital Readmission Prediction in General Internal Medicine
- Systematic Review of Hospital Readmission Prediction Models
- AI-Assisted Radiology Assessment of Cancer: Systematic Review and Meta-Analysis
- Hospital Length of Stay Prediction Methods: Systematic Review
- U.S. FDA: Artificial Intelligence-Enabled Medical Devices
- WHO: Ethics and Governance of AI for Health
- WHO: Ethics and Governance of Large Multimodal Models
Conclusion
Artificial intelligence is moving general hospitals toward a more predictive and connected model of healthcare. The opportunity extends far beyond diagnosis. AI can help hospitals document care, identify deterioration, predict admissions, support emergency triage, analyze medical images, forecast patient flow, reduce administrative work and improve the use of scarce resources.
The research also shows why hospitals should avoid treating AI as a magic solution. Many predictive models demonstrate excellent retrospective performance but have limited prospective evidence. Even strong algorithms can fail if alerts are ignored, data are incomplete or the workflow does not support a clinical response.
The strongest evidence increasingly supports human-AI collaboration. AI can process large volumes of information quickly and identify patterns that may be difficult to detect manually. Healthcare professionals provide context, clinical judgment, accountability and patient-centered decision-making.
For healthcare startups, the opportunity is to build focused AI products that solve measurable hospital problems. For established health systems, the larger opportunity is to create an enterprise AI architecture that connects clinical, operational and administrative intelligence.
Between 2027 and 2030, the most advanced hospitals are likely to move from isolated AI tools toward integrated AI health systems. These systems will continuously analyze patient information, predict demand, support clinicians, automate documentation and coordinate hospital resources.
The future hospital will therefore not be an AI hospital where machines replace healthcare professionals. It will be a human-led health system where AI becomes an intelligent operating layer that helps clinicians make faster decisions, helps organizations use resources more effectively and helps patients receive more connected care.
Leave a Reply