
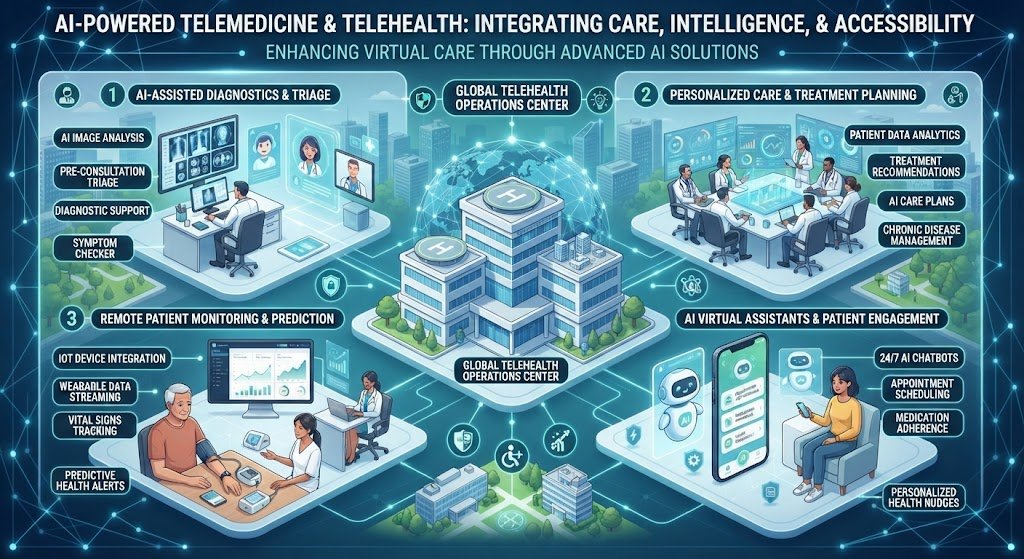
Primary topic: AI in Telemedicine & Telehealth
Research focus: Artificial intelligence in virtual care, AI-powered triage, clinical decision support, virtual diagnosis, medical imaging, remote monitoring, generative AI, clinical documentation, patient engagement, predictive analytics, healthcare automation, privacy, regulation, and the future of AI-enabled telehealth.
AI in Telemedicine & Telehealth: The New Model of Virtual Care
Telemedicine has traditionally focused on connecting patients and healthcare professionals through digital communication. Video consultations, telephone consultations, secure messaging, electronic prescriptions, remote monitoring, and digital follow-up have allowed healthcare organizations to provide services without requiring every patient to physically enter a clinic.
Artificial intelligence is adding another layer to this model.
Instead of simply connecting a patient with a doctor, an AI-enabled telehealth platform can help organize the information that reaches the doctor. It can collect symptoms, summarize medical history, analyze uploaded images, identify patterns in remote monitoring data, prepare documentation, and help determine which cases may need faster attention.
This distinction is important because the biggest opportunity for AI in telehealth is not necessarily replacing the clinician. It is reducing the amount of repetitive work surrounding the clinical encounter and helping healthcare professionals process larger amounts of information.
A telehealth consultation may involve symptoms, medication history, previous diagnoses, laboratory results, images, wearable-device readings, home blood pressure measurements, and information entered by the patient. AI can help structure these different data types before the clinician makes a decision.
A 2025 systematic review examining the integration of AI into telemedicine identified applications including automated diagnostics, predictive analytics, real-time monitoring, chatbots, image analysis, and clinical decision support. The review also highlighted implementation challenges involving ethics, regulation, privacy, data variability, and technology disparities.
Patient → Video / Phone / Messaging → Clinician → Treatment
AI-Enabled Telemedicine
Patient → Data Collection → AI Analysis → Clinician Review → Care Decision → Follow-Up
The second model creates a much broader technology opportunity.
AI becomes part of the complete care journey rather than a separate chatbot or isolated feature.
What the Research Shows About AI in Telehealth
Research on AI-enabled digital health is growing quickly, but the quality of evidence varies considerably between applications.
A 2026 systematic literature review examined 84 clinical studies involving AI-based digital health interventions. Metabolic, musculoskeletal, and mental health conditions represented some of the most common areas of research. The review found that most studies were controlled, but only a small proportion were conducted across multiple countries and many studies had limitations related to sample size and generalizability.
This finding is important for telehealth companies because technical performance alone does not prove clinical benefit.
An AI model may produce accurate predictions in a research environment but behave differently when exposed to patients from another population, lower-quality data, different devices, or a different healthcare system.
Another systematic review of randomized controlled trials found that 30 of 39 included RCTs reported AI-assisted interventions outperforming usual care, while clinically relevant outcomes improved in 21 of those 30 studies. At the same time, the researchers emphasized that the number of RCTs remained limited and heterogeneous.
AI digital-health clinical studies reviewed in a 2026 systematic review
Randomized controlled trials identified in an earlier systematic review
AI interventions that outperformed usual care in the reviewed RCTs
Studies where clinically relevant outcomes improved
The evidence therefore supports continued development, but it also supports a more disciplined approach to implementation.
Telehealth organizations should ask whether an AI system improves the complete healthcare workflow rather than simply asking whether the model has a high accuracy score.
AI-Powered Patient Intake and Pre-Consultation
One of the most practical applications of AI is improving what happens before a telemedicine appointment begins.
Patients often enter symptoms through forms, messages, chat interfaces, or appointment requests. This information may be incomplete, repetitive, or difficult to organize.
AI can transform this unstructured information into a structured clinical summary.
For example, a patient might describe several symptoms in a conversational interface. An AI system can identify the main complaint, duration, severity, associated symptoms, medications, previous conditions, and other relevant information.
The system can then present the information to the healthcare professional before the consultation.
This can reduce the time clinicians spend asking basic administrative questions and allow more attention to the actual clinical conversation.
A large retrospective study of 102,059 virtual primary-care encounters evaluated an AI medical interview system. Providers selected an AI-generated diagnosis in 84.2% of cases, while the top-ranked AI diagnosis was selected in 60.9% of cases. Agreement varied substantially by diagnosis, showing both the potential usefulness of AI-generated clinical information and the importance of diagnosis-specific validation.
Source: Original research on AI diagnostic accuracy in virtual primary care.
AI for Telehealth Triage
Triage is one of the most important and sensitive AI applications in telehealth.
A telehealth platform may receive thousands of patient requests. Some patients need routine care, some require a same-day appointment, and others may need emergency attention.
AI can analyze reported symptoms and help categorize cases according to predefined clinical pathways.
A well-designed triage system should not simply generate a diagnosis. It should determine what action is appropriate within the healthcare organization’s approved workflow.
For example, the output could recommend routine scheduling, urgent clinician review, emergency evaluation, or additional information collection.
Research shows why this area requires caution.
A study comparing ChatGPT, Ada Health, WebMD, and physicians found that diagnostic and triage performance varied between systems. ChatGPT-3.5 produced a relatively high unsafe-triage rate in the study, demonstrating that general-purpose language models should not be assumed to be safe clinical triage systems simply because they can produce fluent medical responses.
A later 2025 study evaluating ChatGPT-4o against expert emergency physicians found moderate-to-substantial agreement overall, with high sensitivity for the most critical and least urgent triage categories but weaker sensitivity for one intermediate category. The researchers concluded that AI could serve as decision support but was not ready to replace professionals.
Patient symptoms
↓
AI information collection
↓
Urgency assessment
↓
Safety rules and escalation checks
↓
Clinician or approved workflow review
↓
Appointment / urgent care / emergency escalation
↓
Follow-up
The most important design principle is that an AI triage recommendation should lead to an appropriate next step.
Source: AI, symptom checker, and physician diagnostic and triage comparison study.
Source: 2025 AI chatbot emergency triage study.
AI for Virtual Diagnosis and Clinical Decision Support
Clinical decision support is another major area for AI-enabled telehealth.
During a virtual consultation, clinicians may have limited access to physical examination findings. This makes the quality and organization of available information especially important.
AI can help summarize medical records, compare symptoms with previous encounters, identify relevant clinical information, and generate differential-diagnosis suggestions.
The clinician can then assess the information using professional judgment.
This approach can be particularly useful in primary care telemedicine, where clinicians manage a wide variety of complaints.
The 102,059-encounter virtual primary-care study provides evidence that AI-generated interviews and differential diagnoses can become part of large-scale virtual-care workflows. The system’s diagnosis was selected by providers in a substantial majority of encounters, but performance varied across conditions.
The key opportunity is therefore not to create an AI doctor that independently treats patients.
The stronger opportunity is to create a clinical intelligence layer that helps a human professional work with information more efficiently.
AI in Teledermatology
Dermatology is particularly suitable for AI-enabled telemedicine because skin conditions can often be documented through photographs.
Patients or healthcare workers can capture images and submit them through a telehealth platform. AI can then help classify or prioritize the image before a dermatologist reviews the case.
Research demonstrates both the promise and the limitations of this approach.
A 2025 review of AI in teledermatology reported that AI-driven solutions can support diagnostic accuracy, triage, decision support, workflow standardization, and resource allocation. The review also identified privacy, algorithmic bias, and regulatory challenges.
A 2026 systematic review and meta-analysis examined 155 teledermatology studies and found pooled diagnostic concordance of 76% across skin conditions and 73% for skin cancers. Dermoscopy improved diagnostic concordance for skin cancers from 67% to 80%. The study also reported high patient satisfaction at 82%.
This creates several AI opportunities.
- Automated image-quality assessment.
- Lesion classification and risk prioritization.
- Dermoscopic image analysis.
- Case prioritization for dermatologist review.
- Longitudinal image comparison.
- Clinical documentation assistance.
- Patient communication and follow-up.
- Referral recommendation support.
An earlier prospective teledermatology study evaluated a 174-class AI system using 340 real-world cases. The algorithm’s overall top-1 accuracy was 41.2%, compared with 60.1% for dermatologists in the reader study. Performance improved when restricted to diagnoses the algorithm had explicitly been trained on, illustrating the importance of defining a system’s intended scope.
Source: AI in Teledermatology review.
Source: 2026 teledermatology diagnostic accuracy meta-analysis.
Source: Prospective real-world teledermatology AI study.
AI in Tele-Ophthalmology
Ophthalmology is another strong environment for AI and telehealth because retinal and other ophthalmic images can be digitally captured and transmitted.
Tele-ophthalmology can allow screening to happen closer to the patient while specialist review or referral remains available when needed.
Diabetic retinopathy is an important example.
A randomized clinical trial comparing telemedicine screening with traditional surveillance found that the telemedicine group was substantially more likely to receive a diabetic retinopathy screening examination during the early follow-up period. The study supported telemedicine as a method for expanding screening access.
AI can add another layer by analyzing retinal images before or alongside professional review.
AI systems can potentially identify diabetic retinopathy, retinal abnormalities, glaucoma-related patterns, and other predefined findings depending on the intended use and validation.
A study of an AI chatbot for ophthalmic triage also demonstrated that AI can perform well on selected clinical vignettes. In that study, GPT-4 identified an appropriate diagnosis within the top three suggestions in 93% of cases and achieved 98% appropriate triage urgency, although such vignette performance should not be interpreted as equivalent to real-world autonomous clinical performance.
The combination of telehealth and computer vision therefore creates a powerful workflow.
↓
IMAGE QUALITY CHECK
↓
AI IMAGE ANALYSIS
↓
RISK / FINDING PRIORITIZATION
↓
CLINICIAN REVIEW
↓
REFERRAL OR FOLLOW-UP
This model can help healthcare systems manage large screening populations without requiring every patient to immediately visit a specialist.
Source: Randomized trial of telemedicine diabetic retinopathy screening.
Source: AI chatbot performance in ophthalmic triage.
AI for Remote Patient Monitoring Through Telehealth
Telemedicine does not have to begin and end with a video consultation.
Remote patient monitoring allows healthcare organizations to receive health information from patients outside traditional clinical environments.
Patients may use blood pressure monitors, glucose sensors, pulse oximeters, ECG devices, smartwatches, patches, scales, or other connected technologies.
AI can analyze these streams of information and identify patterns that may deserve attention.
This is especially relevant for chronic conditions.
A systematic review and meta-analysis of 89 articles examined algorithms used in remote monitoring of chronic conditions. The research found promising performance for algorithms detecting current conditions, particularly arrhythmia and ischemia using ECG data, while evidence for the clinical impact of advanced algorithms remained limited.
A newer 2026 systematic review examined machine learning for predicting disease outcomes from remote monitoring. It included 76 prospective studies and found that 73.7% were considered at high risk of bias, highlighting the difference between having many AI research projects and having strong evidence suitable for broad clinical deployment.
Wearables, home devices, apps, sensors and patient reports
Pattern detection, risk scoring, anomaly detection and forecasting
Care-team evaluation of alerts and patient context
Follow-up, medication review, appointment or escalation
The real value of AI-enabled RPM is therefore not the alert itself.
The value comes from connecting an alert to an appropriate clinical response.
AI for Heart Failure and Chronic Disease Telehealth
Heart failure provides an important example of how AI can support remote care.
Patients may experience changes in weight, heart rate, symptoms, activity, breathing, or other signals before a clinical deterioration becomes obvious.
Researchers and healthcare organizations are exploring AI models that combine these signals to support early detection.
A 2025 review of non-invasive remote monitoring in heart failure discussed wearable devices and AI-based approaches for detecting deterioration and supporting management.
Another 2025 publication explored AI and remote speech analysis as a potential method for detecting worsening heart failure events.
Speech is interesting because it can potentially be collected remotely without requiring a specialized clinical visit.
Changes in voice characteristics could potentially become one component of a larger monitoring model.
Such technology remains an emerging area, but it demonstrates how telehealth is expanding from video communication toward continuous or repeated digital assessment.
Source: Remote monitoring, wearables and AI in heart failure.
Source: AI and remote speech analysis for heart failure monitoring.
Generative AI and Virtual Clinical Documentation
Generative AI is likely to become one of the most visible AI technologies inside telehealth platforms.
Virtual consultations create large amounts of conversational information.
Clinicians may need to document symptoms, assessment, treatment plans, patient instructions, referrals, prescriptions, and follow-up recommendations.
An AI system can listen to an authorized clinical encounter and generate a draft note.
This is commonly known as an ambient AI scribe.
A 2026 scoping review of large language models in clinical documentation identified 41 studies. The applications primarily involved clinical note generation, discharge summaries, and provider-patient encounter documentation. Some studies reported substantial time savings, but factual inaccuracies, hallucinations, privacy concerns, and loss of clinical nuance remained important issues.
A randomized clinical trial involving 238 outpatient physicians across 14 specialties found that use of ambient AI scribes was associated with reductions in physician task load and work exhaustion. One of the evaluated scribes also reduced time spent in notes compared with control. The study nevertheless reported occasional clinically significant inaccuracies, reinforcing the need for physician review.
A 2026 prospective study of an ambient AI scribe integrated with Epic across 23 specialties found that high-frequency users experienced a 21% decrease in daily time spent on notes and a 13% reduction in after-hours documentation time.
Patient + Clinician Conversation
↓
Speech / Audio Processing
↓
AI Clinical Summary
↓
Structured Draft Note
↓
Clinician Review & Correction
↓
Final EHR Documentation
This is one of the strongest near-term opportunities for Generative AI because the system is assisting with documentation rather than independently making the clinical decision.
Source: 2026 systematic review of LLMs in clinical documentation.
Source: Randomized trial of ambient AI scribes.
Source: Prospective ambient AI scribe implementation study.
AI Chatbots and Patient Engagement
AI-powered conversational systems can support patients before and after telehealth appointments.
They can answer approved administrative questions, explain appointment preparation, collect symptoms, remind patients about follow-up, and provide educational information.
Healthcare chatbot research has expanded significantly.
A systematic review of 89 healthcare chatbot articles identified telemedicine, mental health, and medical information as major areas for future development.
The technology becomes more useful when the chatbot is connected to the healthcare organization’s actual workflow.
For example, instead of simply answering “When is my appointment?”, a healthcare chatbot could authenticate the patient, retrieve appointment information, explain preparation instructions, and provide a pathway for requesting a change.
Patient-facing AI can also support multilingual communication.
This can be particularly useful for healthcare organizations serving diverse populations.
However, patient-facing clinical conversations require stronger controls than ordinary customer-service chatbots.
The system needs to distinguish between administrative questions and medical questions.
A question such as “What time is my appointment?” is fundamentally different from “Should I go to the emergency department?”
The second question may require clinical escalation.
AI for Mental Health Telehealth
Mental health is an important area of AI-enabled virtual care because therapy and support can often be delivered through digital communication.
AI conversational agents have been studied for depression, anxiety, psychological distress, psychoeducation, and behavioral support.
A 2025 systematic review of AI mental-health chatbots evaluated 160 studies published between 2020 and 2024. LLM-based systems represented 45% of new studies in 2024, but only 16% of LLM studies had undergone clinical efficacy testing. The researchers emphasized that technical novelty should not be confused with demonstrated therapeutic benefit.
A 2024 meta-analysis of 18 randomized controlled trials involving 3,477 participants found statistically significant improvements in depression and anxiety symptoms with AI chatbot interventions, with the strongest benefits appearing after approximately eight weeks. However, effects were not sustained at three-month follow-up in that analysis.
A newer 2026 systematic review and meta-analysis of commercial AI mental-health chatbots included 52 studies and 22 RCTs involving more than 110,000 participants. The researchers found modest improvements in depressive symptoms, while anxiety results were more uncertain and safety reporting was insufficient in many trials.
These findings suggest that AI can potentially support low-intensity mental-health interventions, but it should not be treated as an unrestricted replacement for professional psychotherapy or crisis care.
Source: 2025 systematic review of AI mental-health chatbots.
Source: AI chatbot depression and anxiety meta-analysis.
Source: 2026 commercial AI mental-health chatbot meta-analysis.
AI for Telehealth Imaging and Computer Vision
Computer Vision Development can become an important part of telehealth where patients or healthcare workers submit images remotely.
Potential applications include dermatology photographs, retinal images, wound images, dental images, radiology images, and other visual data.
The system can perform several different tasks.
- Classification: Identify an image category.
- Detection: Locate a suspected abnormality.
- Segmentation: Outline a specific structure or region.
- Measurement: Estimate size, shape, distance, or other visual characteristics.
- Quality assessment: Determine whether an image is usable.
- Change detection: Compare current and previous images.
- Prioritization: Move potentially important cases higher in the review queue.
The image-quality component deserves particular attention.
Poor images can reduce AI performance and can also make remote diagnosis difficult for human clinicians.
A telehealth platform should therefore consider image quality as part of the clinical workflow rather than assuming that every patient-submitted image is usable.
Research in teledermatology demonstrates this clearly. Diagnostic reliability improves when high-quality images and appropriate image-acquisition techniques are used.
AI for Predictive Analytics in Telehealth
Predictive analytics moves telehealth from reactive care toward proactive care.
Instead of waiting for a patient to report deterioration, an AI system can analyze historical and current information to identify patterns associated with increased risk.
Possible prediction targets include:
- Risk of hospital admission.
- Risk of clinical deterioration.
- Risk of missed appointments.
- Likelihood of treatment non-adherence.
- Probability of follow-up completion.
- Potential escalation needs.
- Expected demand for virtual appointments.
- Potential need for specialist referral.
- Patient disengagement from digital programs.
- Expected rehabilitation or chronic-care outcomes.
However, predictive analytics must be evaluated carefully.
A prediction is not the same as a clinical outcome.
If a model predicts high risk, the organization must know what intervention will follow.
A useful predictive system therefore connects the model with an operational pathway.
↓
Machine Learning Model
↓
Risk Score / Prediction
↓
Clinical Threshold
↓
Human Review
↓
Intervention
↓
Outcome Measurement
AI Workflow Automation for Telehealth Providers
Telehealth organizations handle much more than clinical consultations.
There are appointment requests, reminders, cancellations, referrals, insurance questions, documentation, follow-up tasks, patient messages, provider notifications, and administrative workflows.
AI Workflow Automation can connect these activities.
For example, when a patient completes a virtual appointment, an AI-enabled workflow could identify whether a follow-up appointment is needed, prepare a patient message, create a task for the care team, and organize the relevant information for review.
Other potential applications include:
- Appointment scheduling and rescheduling.
- Automated patient reminders.
- Referral intake and routing.
- Prior-authorization information gathering.
- Patient message classification.
- Follow-up task generation.
- Missed-appointment outreach.
- Prescription refill workflow support.
- Clinical documentation preparation.
- Patient education delivery.
- Care-program enrollment.
- Operational reporting.
The important distinction is that workflow automation can reduce administrative workload without requiring AI to make the underlying medical decision.
AI Integration With EHR and Telehealth Infrastructure
The success of AI in telemedicine will depend heavily on integration.
A healthcare organization may already use an EHR, telehealth video platform, scheduling software, patient portal, laboratory system, imaging platform, billing system, CRM, and remote-monitoring devices.
Introducing another disconnected AI application can create additional work rather than reducing it.
A stronger architecture places AI inside the existing healthcare ecosystem.
↓
Integration & Interoperability Layer
↓
EHR + Patient Portal + Scheduling + Imaging + RPM
↓
AI Models + Generative AI + Analytics
↓
Clinical Workflow
↓
Human Review + Audit Trail
AI Integration and Deployment should therefore be considered during the initial architecture stage.
Authentication, access control, data transmission, audit logs, data retention, API connectivity, and security should be designed alongside the AI functionality.
AI Capability Map for Telemedicine & Telehealth
| AI Capability | Telehealth Application | Primary Value |
|---|---|---|
| AI Development | Virtual-care platforms and clinical intelligence | Product differentiation |
| Machine Learning | Risk prediction and clinical forecasting | Proactive care |
| Computer Vision | Teledermatology, tele-ophthalmology and remote imaging | Image analysis |
| Generative AI | Clinical summaries, notes and patient communication | Documentation efficiency |
| AI Triage | Symptom assessment and care routing | Access and prioritization |
| AI Workflow Automation | Scheduling, referrals, recalls and follow-up | Operational efficiency |
| AI Integration | EHR, patient portal, RPM and telehealth systems | Workflow adoption |
| Data Analytics | Provider, patient and operational intelligence | Better decisions |
Responsive AI Architecture for Modern Telehealth
Mobile app, browser, video consultation, messaging, wearable devices and patient-submitted information.
LLMs, machine learning, computer vision, speech processing and predictive analytics.
Clinicians, care teams, escalation rules, review workflows and clinical decision-making.
EHR, scheduling, billing, analytics, authentication, APIs, audit logs and security.
This architecture allows a telehealth company to add AI capabilities without redesigning the entire healthcare platform.
Major Challenges Facing AI in Telehealth
AI adoption in telemedicine has several challenges that healthcare organizations need to address before large-scale deployment.
Clinical reliability is the first concern. AI can make incorrect predictions, miss important findings, or produce plausible but inaccurate language.
Data quality is another major issue. Patient-generated data may be incomplete, inconsistent, incorrectly measured, or collected using different devices.
Bias and generalizability can affect performance across populations. A model developed using one patient population may not perform equally well in another.
Privacy and security become especially important because telehealth involves remote transmission of sensitive health information. HHS guidance identifies risks such as unauthorized access, data breaches, and improper handling of patient information.
Integration is a practical challenge because healthcare organizations often have fragmented technology environments.
Workflow design can also determine whether AI succeeds. If an AI system generates too many alerts, clinicians may ignore them. If it generates information without a clear next action, it may create additional workload.
Patient trust is another factor. Patients need to understand when AI is being used and whether a human professional is reviewing the result.
Regulation and Governance of AI Telehealth
AI used for healthcare can fall into very different regulatory categories depending on what it does.
A general administrative chatbot may have a very different regulatory profile from an AI system that interprets medical images or provides clinical decision support.
The intended use of the technology matters.
The FDA maintains a public list of AI-enabled medical devices authorized for marketing in the United States. The agency explains that listed devices have gone through applicable premarket requirements and that the list is intended to improve transparency around AI-enabled medical technology.
The FDA’s software guidance resources also address areas such as cybersecurity and lifecycle management for medical-device software.
The WHO’s guidance on AI for health emphasizes ethics, human rights, accountability, transparency, and responsible governance.
Intended Use
↓
Risk Classification
↓
Clinical Validation
↓
Privacy & Security Review
↓
Human Oversight
↓
Controlled Deployment
↓
Performance Monitoring
↓
Model / Workflow Updates
Healthcare providers should establish governance before allowing AI to become deeply embedded across virtual-care operations.
Economic and Operational Opportunity
The business case for AI in telehealth should not be based only on the promise of lower costs.
The strongest business case usually comes from combining several improvements.
A telehealth company may increase provider capacity by reducing documentation time.
It may improve patient access through automated intake.
It may reduce unnecessary manual review through intelligent prioritization.
It may improve follow-up by identifying patients who have not completed recommended actions.
It may create additional value by analyzing remote-monitoring data.
It may also improve clinician experience.
Research into ambient AI documentation provides evidence that documentation-focused AI can reduce time and workload in some clinical settings.
For a telehealth provider, useful business metrics can include:
- Average consultation preparation time.
- Documentation time per encounter.
- Provider capacity.
- Patient wait time.
- Appointment completion rate.
- Follow-up completion rate.
- Referral turnaround time.
- Patient satisfaction.
- Clinician satisfaction.
- Cost per virtual encounter.
- AI-related operational savings.
- Clinical quality and safety indicators.
AI Opportunity Matrix for Telemedicine
| Use Case | AI Technology | Potential Impact | Human Review |
|---|---|---|---|
| Patient intake | Generative AI + NLP | High | Recommended |
| Triage | ML + clinical rules + NLP | Very High | Essential for high-risk cases |
| Image analysis | Computer Vision | Very High | Depends on intended use |
| Remote monitoring | ML + anomaly detection | High | Essential for alerts |
| Documentation | Generative AI | Very High | Essential |
| Patient messaging | LLM + knowledge base | High | Policy-dependent |
| Referral prioritization | ML + rules | High | Recommended |
| Operational analytics | ML + analytics | Medium to High | Management review |
Future of AI in Telemedicine & Telehealth
The future of telehealth is likely to be more continuous, intelligent, and connected.
The video consultation will remain important, but it will become one component of a larger digital-care ecosystem.
AI will increasingly work before the consultation, during the consultation, and after the consultation.
Before the consultation, AI can collect and organize information.
During the consultation, AI can assist with documentation, information retrieval, and clinical decision support.
After the consultation, AI can help with follow-up, patient education, referral workflows, and remote monitoring.
Multimodal AI Will Become More Important
Future telehealth systems will increasingly combine text, voice, images, physiological measurements, medical records, and patient-generated data.
A dermatologist may use patient photographs plus clinical history.
A cardiology platform may combine ECG signals, symptoms, activity data, and previous clinical information.
An ophthalmology platform may combine retinal images with patient history.
A virtual primary-care system may combine conversational information, medication data, laboratory results, and wearable measurements.
This creates an opportunity for multimodal AI systems that can reason across several data types.
AI Agents Will Automate Multi-Step Healthcare Workflows
Current AI tools often perform individual tasks.
Future systems will increasingly coordinate multiple tasks.
An AI agent could receive a patient request, collect structured information, check approved workflow criteria, prepare a summary, route the case, generate administrative communication, and create a follow-up task.
The healthcare organization can define which steps require human approval.
This model could significantly expand the operational capabilities of telehealth platforms.
Remote Monitoring Will Become More Intelligent
Wearables and connected medical devices are becoming more capable of collecting health information outside clinical environments.
The FDA maintains a growing list of authorized sensor-based digital-health devices, including wearable and home-monitoring technologies capable of continuous or spot-check monitoring.
As more data becomes available, AI can help identify meaningful patterns.
The challenge will be avoiding alert overload.
A future RPM system should not simply generate more notifications.
It should prioritize the alerts that are most likely to require action.
Telehealth Will Become More Personalized
AI can analyze individual patient histories and patterns to help personalize communication, monitoring, reminders, and care pathways.
A patient with repeated missed appointments may receive a different engagement workflow from a patient who consistently follows the recommended schedule.
A chronic-care patient whose measurements are stable may receive routine monitoring, while a patient showing concerning changes may be prioritized for clinician review.
Personalization can therefore apply to both clinical and operational processes.
Recommendations for Telehealth Providers
Healthcare organizations should start with a clearly defined problem.
The best first AI project is rarely “build an AI telehealth platform.”
A stronger starting point is “reduce documentation time,” “improve patient intake,” “prioritize remote-monitoring alerts,” or “improve referral processing.”
The organization should establish a baseline before deployment.
It should measure how long the existing process takes, how many staff members are involved, how many errors occur, and what outcome the organization wants to improve.
The next step should be validation.
The AI system should be tested using representative data and realistic workflows.
High-risk clinical applications require substantially stronger validation than low-risk administrative automation.
Integration should then become part of the implementation plan.
The AI system should connect with the EHR, patient portal, scheduling system, telehealth platform, or other relevant infrastructure rather than creating another disconnected workflow.
Finally, the organization should monitor performance after launch.
AI systems can behave differently after deployment because patients, devices, clinical practices, and data distributions change.
→
DATA
→
AI MODEL
→
VALIDATION
→
INTEGRATION
→
CLINICIAN WORKFLOW
→
MEASUREMENT
→
IMPROVEMENT
Key Performance Metrics for AI Telehealth
| Area | Metrics to Track |
|---|---|
| Clinical Quality | Diagnostic agreement, sensitivity, specificity, missed findings, escalation accuracy |
| Patient Access | Waiting time, appointment availability, completed consultations |
| Provider Efficiency | Documentation time, consultation preparation time, workload |
| Patient Experience | Satisfaction, engagement, response time, follow-up completion |
| Safety | Unsafe triage, adverse events, incorrect outputs, escalation failures |
| Financial | Cost per encounter, staff time, productivity, utilization and ROI |
| Technical | System uptime, latency, integration failures, model drift and data quality |
What This Means for Healthcare Startups
Healthcare startups have a major opportunity to build AI-enabled telehealth products around specific clinical workflows.
A startup does not necessarily need to compete by building another general-purpose medical chatbot.
More focused opportunities may include AI-assisted triage, remote-monitoring analytics, teledermatology image analysis, tele-ophthalmology screening, clinical documentation, referral automation, patient engagement, and predictive care management.
The strongest products may combine several AI capabilities.
For example, Computer Vision Development can analyze an image, Machine Learning can estimate risk, Generative AI can create a structured explanation, and AI Workflow Automation can route the result to the correct healthcare professional.
That creates a complete workflow rather than a standalone model.
Startups should also design clinical validation into the product roadmap.
The research literature repeatedly demonstrates that promising algorithmic performance does not automatically translate into proven clinical benefit. The 2026 evidence reviews of AI digital health and remote monitoring both emphasize limitations involving generalizability, bias, external validation, and clinical-outcome evidence.
A healthcare AI startup should therefore build around this sequence:
↓
REPRESENTATIVE DATA
↓
AI DEVELOPMENT
↓
CLINICAL VALIDATION
↓
SECURE INTEGRATION
↓
HUMAN-AI WORKFLOW
↓
REAL-WORLD OUTCOMES
This approach is more likely to create a product that healthcare organizations can trust and actually use.
What This Means for Existing Healthcare Organizations
Established healthcare organizations already have something many startups lack: real workflows and historical data.
Hospitals, clinics, physician groups, and telehealth companies may already have years of appointment records, patient communications, clinical documentation, imaging, remote-monitoring information, and operational data.
The challenge is converting that data into useful intelligence while protecting patient privacy and maintaining clinical accountability.
Organizations should not attempt to automate everything at once.
A controlled pilot can begin with a low-risk workflow such as documentation, patient intake, appointment communication, or operational analytics.
Once the organization has evidence that the system works, it can consider more complex applications such as clinical decision support or remote-monitoring prediction.
This staged approach reduces implementation risk and gives clinicians time to understand how AI affects their work.
Overall Research Conclusion
Artificial intelligence is becoming an important technology layer for telemedicine and telehealth.
The technology can improve patient intake, support triage, analyze medical images, process remote-monitoring data, assist clinical decision-making, automate documentation, personalize communication, and improve operational workflows.
The research evidence is strongest when AI is used for clearly defined tasks with measurable outcomes.
At the same time, research also demonstrates why healthcare organizations should avoid treating AI accuracy claims as proof of clinical safety.
Symptom-checker studies have shown substantial variation in diagnostic and triage performance. Teledermatology research demonstrates that image quality and clinical expertise affect results. Remote-monitoring reviews show that strong predictive performance does not automatically prove improved patient outcomes. Generative AI documentation studies show productivity benefits alongside the need for continued review.
The future of telehealth will therefore not simply be about adding AI chatbots to video platforms.
It will be about building connected healthcare systems in which AI supports the entire patient journey.
AI will increasingly collect information before the consultation, support clinicians during the encounter, monitor patients between visits, automate administrative workflows, and identify opportunities for earlier intervention. The most successful systems will combine AI development, machine learning, computer vision, generative AI, predictive analytics, secure integration, and human clinical oversight into one measurable workflow.
Credible Data Sources and Original Research
- AI and Telemedicine: A 2025 systematic review examined AI applications in telemedicine, including diagnostics, predictive analytics, monitoring, chatbots, and implementation challenges. Source: Original research on PubMed.
- AI Digital Health Evidence: A 2026 systematic literature review analyzed 84 clinical studies evaluating AI-based digital health interventions and highlighted gaps in generalizability and clinical validation. Source: Original 2026 systematic review.
- AI in Clinical Practice: A systematic review of randomized controlled trials found that 30 of 39 RCTs reported AI-assisted interventions outperforming usual clinical care. Source: Original RCT systematic review.
- Virtual Primary Care: A large retrospective study analyzed 102,059 virtual primary-care encounters involving an AI medical interview and AI-supported differential diagnosis. Source: Original virtual-care AI study.
- AI Triage: A clinical data analysis study compared ChatGPT, Ada Health, WebMD, and physicians for diagnosis and triage of emergency-department cases. Source: Original AI triage research.
- Emergency AI Triage: A 2025 study evaluated ChatGPT-4o against expert emergency physicians across 60 emergency case scenarios. Source: Original 2025 AI triage study.
- Teledermatology: A 2026 systematic review and meta-analysis evaluated 155 studies and found pooled diagnostic concordance of 76% across skin conditions and 73% for skin cancers. Source: Original teledermatology meta-analysis.
- AI Teledermatology: A prospective study evaluated a 174-class AI algorithm in real-world teledermatology and compared its performance with dermatologists, residents, and general practitioners. Source: Original prospective teledermatology AI study.
- Teledermatology Reliability: A systematic review and meta-analysis examined diagnostic agreement between teledermatology and face-to-face dermatology. Source: Original diagnostic reliability review.
- Tele-Ophthalmology: A randomized clinical trial evaluated telemedicine versus traditional surveillance for diabetic retinopathy screening. Source: Original long-term telemedicine trial.
- Ophthalmic AI Triage: A study compared ChatGPT, Bing Chat, WebMD, and ophthalmology trainees for diagnosis and triage of ophthalmic conditions. Source: Original ophthalmology AI study.
- Remote Monitoring Algorithms: A systematic review and meta-analysis evaluated 89 articles on algorithmic remote monitoring of chronic conditions and found promising performance in selected diagnostic applications but limited evidence connecting algorithm performance to clinical impact. Source: Original remote-monitoring research.
- Machine Learning and Remote Monitoring: A 2026 systematic review assessed 76 prospective studies using machine learning to predict outcomes from remote monitoring and found substantial methodological limitations. Source: Original 2026 systematic review.
- AI Clinical Documentation: A 2026 scoping review analyzed 41 studies on large language models in clinical documentation and reported potential efficiency improvements alongside concerns about inaccuracies, hallucinations, privacy, and clinical nuance. Source: Original LLM documentation review.
- Ambient AI Scribes: A randomized clinical trial involving 238 outpatient physicians across 14 specialties evaluated the effect of ambient AI scribes on documentation time, workload, and work exhaustion. Source: Original randomized ambient-AI study.
- Ambient AI Implementation: A prospective study integrated an AI note-writing platform with Epic across 23 specialties and measured changes in documentation time and after-hours work. Source: Original implementation study.
- Heart Failure Monitoring: A 2025 review examined non-invasive remote monitoring, wearable devices, and artificial intelligence approaches in heart failure. Source: Original heart-failure AI review.
- AI Speech Monitoring: Research examined the potential use of remote speech analysis with AI to detect worsening heart failure events. Source: Original heart-failure speech-monitoring research.
- WHO: WHO guidance provides principles for ethical, safe, accountable, and human-rights-centered use of artificial intelligence in health. Source: WHO Ethics and Governance of AI for Health.
- FDA: The FDA maintains a public list of AI-enabled medical devices authorized for marketing in the United States and provides regulatory and safety information for AI-enabled healthcare technologies. Source: FDA AI-Enabled Medical Devices.
- HHS: HHS telehealth guidance addresses privacy and security risks associated with collecting, transmitting, and storing sensitive patient information through telehealth technologies. Source: HHS Telehealth Privacy and Security Guidance.
- CMS: CMS maintains the Medicare telehealth framework and updates the list of services payable under the Medicare Physician Fee Schedule. Source: CMS 2026 Telehealth Services.
Leave a Reply