
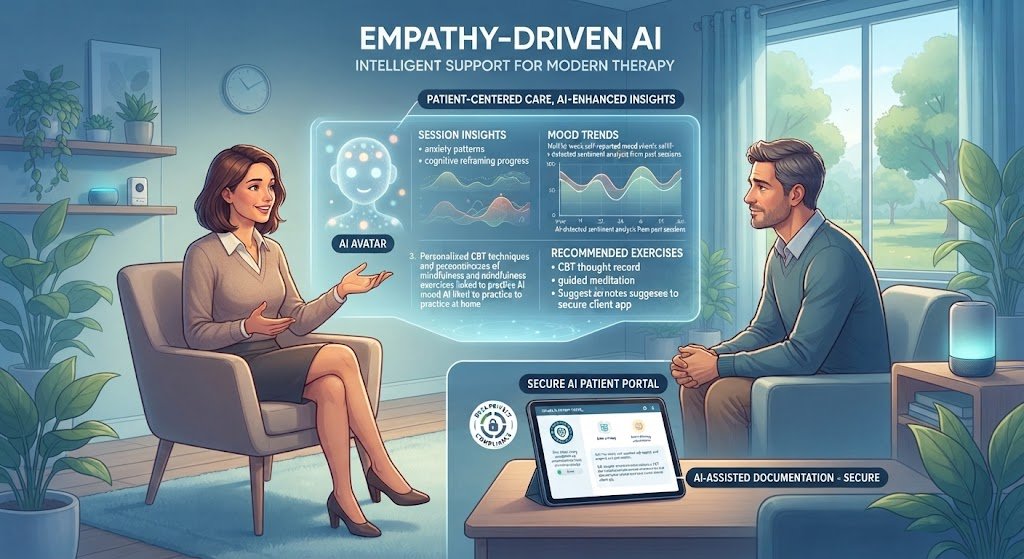
Artificial intelligence is becoming a new layer in mental health and psychotherapy rather than a replacement for therapists. The strongest near-term applications are AI-assisted documentation, patient intake, screening support, psychoeducation, outcome monitoring, workflow automation and structured between-session support. Research on conversational AI is also becoming stronger, with randomized trials and meta-analyses reporting improvements in depression, anxiety and psychological well-being. However, clinical evidence remains uneven, particularly for newer generative AI systems. The next phase of mental health AI will depend on clinical validation, human oversight, privacy protection, crisis escalation, culturally appropriate models and integration with real healthcare workflows.
AI in Mental Health: Current Trends & Future Predictions
Mental health care is entering a major technology transition. Artificial intelligence is moving beyond simple wellness applications and into clinical documentation, digital interventions, screening, patient monitoring, psychotherapy support and research.
The timing is important. More than one billion people now live with a mental health condition globally, while healthcare systems continue to face shortages of trained professionals and limited funding. WHO’s 2024 Mental Health Atlas found a global median of only 13.5 specialized mental health workers per 100,000 people, while median government spending on mental health remained close to 2% of total health budgets.
This creates a clear technology opportunity, but mental health is also one of the highest-risk areas for poorly designed AI. A chatbot that gives an incorrect restaurant recommendation may be inconvenient. A mental health system that gives unsafe advice to a person in crisis can be dangerous.
For that reason, the most important question is not whether AI can talk like a therapist. The more useful question is where AI can safely improve access, continuity, personalization, documentation and clinical decision support while keeping qualified professionals responsible for high-risk decisions.
Key Research Findings
- More than 1 billion people globally live with a mental health condition, creating a major capacity problem for healthcare systems.
- Only about 2% of government health budgets are allocated to mental health globally, according to WHO’s latest Mental Health Atlas data.
- 13.5 specialized mental health workers per 100,000 people is the global median, with much lower availability in low-income settings.
- A systematic review of 160 AI mental health chatbot studies published between 2020 and 2024 found that LLM-based systems represented 45% of new studies in 2024.
- However, only 16% of LLM chatbot studies in that review had reached clinical efficacy testing, showing that technological development is moving faster than clinical validation.
- A 2025 meta-analysis of 14 randomized trials involving 6,314 participants found a statistically significant overall effect from generative AI mental health chatbots.
- A newer meta-analysis covering 39 randomized studies found significant reductions in depressive and anxiety symptoms from mental health chatbots.
- A 2026 randomized trial involving 995 university students found that conversational AI improved anxiety, depression and well-being compared with control conditions.
- Speech-based depression detection research has produced pooled diagnostic accuracy around 87% in one meta-analysis, but performance varies across languages, datasets and validation methods.
- The strongest near-term business opportunity is likely to be AI-assisted care, not autonomous psychotherapy.
Why Mental Health Is Becoming an AI Priority
The global mental health gap is too large to solve through traditional specialist care alone. WHO reports that more than one billion people live with mental health conditions, while many do not receive adequate treatment. Mental health conditions are among the leading causes of disability, and suicide remains a major public health issue.
At the same time, resources remain limited. WHO reports that the median share of government health spending dedicated to mental health is around 2%, unchanged from previous reporting periods. The global median mental health workforce is only 13.5 specialized workers per 100,000 population.
The Global Mental Health Capacity Gap
People living with mental health conditions
More than 1 billion people
Government health spending on mental health
About 2%
Global specialized mental health workforce
13.5 per 100,000 population
Business implication: AI does not need to replace clinicians to create value. Increasing the capacity of each clinician can itself become a major healthcare opportunity.
Research Evidence: What Do We Actually Know?
One of the biggest problems in AI mental health research is that the term “AI” covers very different technologies. A rule-based chatbot, a machine-learning prediction model and a large language model should not be treated as the same clinical technology.
A 2025 systematic review in World Psychiatry examined 160 studies published between 2020 and 2024. The review found a rapid shift toward LLM-based systems. LLM chatbots represented 45% of new studies in 2024, but only 16% of LLM studies had undergone clinical efficacy testing. About 77% remained in early validation stages.
This creates an important evidence gap. Technical capability is developing faster than clinical proof.
AI Mental Health Evidence Pipeline
Can the AI system technically perform the task?
Will patients and clinicians actually use it?
Does it improve measurable mental health outcomes?
Does it remain safe and effective across different populations and clinical settings?
Research Analysis 1: Generative AI Chatbots
Generative AI chatbots are receiving the most attention because they can conduct open-ended conversations rather than relying entirely on predefined scripts.
A 2025 systematic review searched 11 databases and screened 5,555 records before conducting a meta-analysis of 14 randomized controlled trials involving 6,314 participants. The pooled effect size was 0.30, which was statistically significant. The researchers also found that socially oriented chatbots performed better than task-oriented systems in the included evidence.
The result is promising but should not be overstated. The prediction interval was wide, and the authors highlighted the relatively small number of rigorous trials. This means that the average result cannot guarantee the same outcome for every patient or every AI system.
The practical conclusion is that generative AI can potentially provide useful low-intensity psychological support, but healthcare organizations should not assume that conversational fluency equals therapeutic effectiveness.
What This Research Means for Clinics
- Use AI for structured support rather than unrestricted autonomous treatment.
- Measure actual patient outcomes rather than chatbot engagement alone.
- Separate wellness support from clinical treatment claims.
- Use escalation rules when symptoms indicate a need for professional intervention.
- Validate the system with the actual population it will serve.
Research Analysis 2: Depression and Anxiety Outcomes
The evidence base for mental health chatbots is becoming larger. A 2026 systematic review and meta-analysis included 39 eligible studies. Thirty-eight studies involving 7,401 participants contributed to the depression analysis, while 34 studies involving 7,621 participants contributed to the anxiety analysis.
The pooled effect size was 0.31 for depressive symptoms and 0.28 for anxiety symptoms. Both results were statistically significant compared with control conditions. The effects were larger in clinical and subclinical populations than in nonclinical samples.
Chatbot Research: Depression vs Anxiety
| Outcome | Studies / Participants | Pooled Effect | Interpretation |
|---|---|---|---|
| Depression | 38 studies / 7,401 | g = 0.31 | Significant improvement |
| Anxiety | 34 studies / 7,621 | g = 0.28 | Significant improvement |
Important: Effect size measures group-level differences. It does not mean that every individual patient will experience the same improvement.
Research Analysis 3: AI Compared With Face-to-Face Group Therapy
One of the most interesting recent developments is research directly comparing conversational AI with established forms of psychological support.
A 2026 randomized clinical trial included 995 university students experiencing psychological distress. Participants were assigned to a conversational AI intervention, face-to-face group therapy or a waiting-list control. The study followed participants through a 12-week intervention and a three-month follow-up period.
The AI group experienced greater anxiety reduction than both group therapy and the waiting-list control. Depression also improved more than the waiting-list control, while well-being improved compared with both comparison groups.
The study is important because it moves the discussion beyond whether people enjoy chatting with AI. It evaluates measurable psychological outcomes.
However, the population was university students experiencing psychological distress. The findings should therefore not be generalized to severe psychiatric illness, crisis care or all psychotherapy populations.
Why Therapeutic Alliance Matters
The study also found a relationship between perceived therapeutic alliance, engagement and symptom improvement. This suggests that people do not necessarily respond only to information. The perceived quality of the relationship with the system can influence how much they use it and whether they benefit.
This creates an important product-design challenge. Future AI systems will need to balance personalization with boundaries. An AI should feel supportive without misleading users into believing that it is a human therapist.
Research Analysis 4: AI for Young People
Young people are an important population for digital mental health because they are often comfortable using conversational technology, but they also require additional safeguards.
A 2025 systematic review and meta-analysis examined 14 articles containing 15 trials and 1,974 participants. After adjustment for publication bias, AI conversational agents showed a moderate-to-large effect on depressive symptoms, with Hedges’ g of 0.61. However, the adjusted effects for generalized anxiety, stress, positive affect, negative affect and mental well-being were not statistically significant.
This is a good example of why AI research needs outcome-specific analysis. A system may help with depression without producing the same level of benefit for anxiety or general well-being.
The evidence also highlights the need for longer follow-up periods. Short-term symptom improvement does not automatically prove that an intervention creates durable mental health benefits.
Research Analysis 5: Speech AI and Depression Detection
Another major research area is AI-based analysis of speech. Researchers are examining pitch, pauses, speaking rate, acoustic characteristics and linguistic patterns that may correlate with depression.
A systematic review and meta-analysis identified 25 studies, with eight included in the quantitative analysis. The pooled accuracy of deep-learning models was 87%, while pooled sensitivity was 82% and specificity was 85%.
A newer 2025 meta-analysis of 25 studies found that traditional machine-learning models produced pooled sensitivity of 82%, specificity of 83% and AUC of 0.89. Deep-learning models achieved sensitivity of 83%, specificity of 86% and AUC of 0.91.
Speech AI Diagnostic Performance
| Model Type | Sensitivity | Specificity | AUC |
|---|---|---|---|
| Traditional ML | 82% | 83% | 0.89 |
| Deep Learning | 83% | 86% | 0.91 |
Key limitation: Performance changes according to language, diagnostic criteria, sample size and validation strategy. A model trained on one population cannot automatically be assumed to work equally well in another.
Research Analysis 6: AI for Suicide Risk Prediction
Suicide risk prediction is one of the most sensitive areas of mental health AI. Machine-learning systems can analyze large quantities of clinical data and identify statistical patterns that may be difficult to detect manually.
However, prediction of rare events creates a major statistical challenge. Even a model with high overall accuracy can produce many false positives when the event being predicted is relatively uncommon.
For this reason, AI should not produce a simple autonomous decision such as “low risk” or “high risk” and end the workflow. A safer design is to use AI to identify signals that require structured professional assessment.
Safer AI Risk Workflow
Patient Data → AI Signal Detection → Risk Flag → Human Clinical Review → Structured Assessment → Safety Plan / Escalation → Follow-Up
The AI system should therefore be treated as an early-warning layer rather than the final authority. Crisis intervention, emergency referral and clinical responsibility must remain outside the generative model.
Research Analysis 7: Commercial Mental Health AI
Commercial AI mental health tools are expanding rapidly, but the evidence is more complicated than marketing claims often suggest.
A 2026 systematic review and meta-analysis included 52 studies, including 22 randomized controlled trials, covering 13 commercial mental health chatbots and more than 110,000 participants across the broader evidence base.
For depression, 18 randomized trials involving 3,170 participants produced a pooled effect size of -0.35. The estimated improvement was approximately 1.6 points on the PHQ-9, below the commonly cited five-point threshold for minimal clinically important difference. Anxiety effects were uncertain.
This distinction is extremely important for healthcare startups. A statistically significant result can still represent a small clinical change.
What AI Can Actually Do in a Mental Health Practice
The opportunity extends far beyond AI therapy. A modern mental health organization can use AI across almost every stage of the patient journey.
| Practice Area | AI Capability | Potential Value |
|---|---|---|
| Patient Intake | Conversational intake and structured history | Less administrative work |
| Screening | Questionnaire analysis and trend detection | Faster assessment preparation |
| Documentation | Ambient clinical notes | Reduced documentation burden |
| Therapy | Structured therapeutic exercises | Between-session support |
| Monitoring | Longitudinal symptom analysis | Earlier identification of deterioration |
| Research | Literature and dataset analysis | Faster evidence review |
| Operations | Scheduling and workflow automation | Lower operational workload |
| Patient Education | Personalized educational content | Better understanding and engagement |
15 High-Value AI Use Cases
1. AI-Powered Patient Intake
Patients can provide information conversationally before an appointment. AI can transform unstructured answers into a structured summary for the therapist or psychiatrist.
2. Automated Clinical Documentation
Ambient AI can convert therapy conversations into draft clinical notes. The clinician reviews, corrects and approves the final record.
3. Screening and Assessment Support
AI can organize results from validated tools such as PHQ-9, GAD-7 and other standardized assessments while highlighting changes over time.
4. Personalized Psychoeducation
AI can explain conditions, treatment concepts and behavioral strategies in language appropriate to the patient’s age, literacy and preferred language.
5. Between-Session Therapy Support
AI can remind patients about agreed exercises, journaling, behavioral activation or other clinician-approved activities.
6. CBT Support
AI can guide structured thought records, identify cognitive patterns and help patients complete clinician-approved exercises.
7. Mood and Symptom Monitoring
AI can identify changes in patient-reported symptoms and generate longitudinal summaries for clinicians.
8. Speech Analysis
Machine learning can analyze speech characteristics as an additional research or assessment signal.
9. Risk Signal Detection
AI can flag predefined language or behavioral patterns that require human review and escalation.
10. Therapist Copilot
A clinical AI assistant can summarize previous sessions, organize treatment goals and prepare information before the next appointment.
11. Clinical Research Assistant
AI can summarize scientific literature, compare studies, extract outcome measures and help researchers organize evidence.
12. Referral Automation
AI can route patients according to predefined clinical and administrative criteria while keeping clinical approval in the workflow.
13. Appointment Optimization
Predictive analytics can help clinics identify likely no-shows, optimize scheduling and automate reminders.
14. Multilingual Mental Health Support
AI translation can make educational and administrative resources available across languages, although culturally sensitive clinical communication still requires human oversight.
15. Population Mental Health Analytics
Aggregated data can help organizations identify demand patterns, treatment outcomes and service gaps without exposing unnecessary patient-level information.
AI Capability Map
| Technology | Mental Health Application | Current Maturity |
|---|---|---|
| Generative AI | Conversation, education, summaries | High / rapidly evolving |
| Natural Language Processing | Notes, text analysis, documentation | High |
| Machine Learning | Risk and outcome prediction | Medium / research-heavy |
| Speech AI | Depression and behavioral signal analysis | Emerging |
| Predictive Analytics | Patient trajectories and outcomes | Medium |
| Workflow Automation | Scheduling, referrals, follow-ups | Very High |
| Computer Vision | Behavioral and research applications | Emerging |
The Future Mental Health AI Workflow
AI-Enabled Mental Health Care Journey
Patient Discovery
↓
AI Intake & Scheduling
↓
Validated Screening
↓
Clinician Assessment
↓
Personalized Treatment Plan
↓
Therapy + AI-Assisted Between-Session Support
↓
Continuous Outcome Monitoring
↓
AI Risk / Deterioration Signals
↓
Clinician Review
↓
Escalation or Treatment Adjustment
↓
Longitudinal Outcome Measurement
AI and the Future of Psychotherapy Practice
The future psychotherapy clinic will likely not be an “AI therapist clinic.” It will be a human-led practice with an AI operating layer.
The therapist may begin the day with an AI-generated summary of patients whose symptoms have changed. Before each session, the system could summarize previous goals and outcomes. During the session, an ambient documentation system could prepare a draft note. Afterward, AI could help generate personalized homework or educational material approved by the clinician.
This changes the economics of care. Instead of trying to replace a therapist, AI can increase the amount of useful work a therapist can complete within the same working day.
Human vs AI Responsibilities
| AI Should Primarily Handle | Clinicians Should Own |
|---|---|
| Information organization | Diagnosis |
| Documentation drafts | Treatment decisions |
| Trend detection | Clinical interpretation |
| Educational content | Therapeutic relationship |
| Administrative automation | High-risk assessment |
| Workflow alerts | Crisis intervention |
Major Industry Trends
Trend 1: From Chatbots to AI Clinical Platforms
The market is moving from standalone chatbots toward integrated systems combining conversation, documentation, patient monitoring, clinical data and workflow automation.
Trend 2: Multimodal Mental Health AI
Future systems will combine text, speech, questionnaires, behavioral signals and potentially wearable data. This could provide a more longitudinal view of patient well-being than one-time appointments.
Trend 3: AI Documentation Will Scale Faster Than Autonomous Therapy
Documentation and administrative automation have a lower clinical risk profile than autonomous psychotherapy. This makes them likely to become mainstream earlier.
Trend 4: Evidence Will Become a Competitive Advantage
The growing number of AI mental health products will make evidence quality increasingly important. Healthcare organizations will need to distinguish between marketing claims, technical benchmarks, user engagement and clinically meaningful outcomes.
Trend 5: Human Oversight Will Become Embedded in Product Design
High-risk AI systems will increasingly require explicit clinician review, audit trails, escalation mechanisms and the ability to override AI recommendations.
Trend 6: Personalized Digital Therapeutics
AI can adjust educational content, reminders and behavioral exercises according to a patient’s progress. The long-term opportunity is not simply personalization of conversation, but personalization of the entire care journey.
Safety, Ethics and Governance
Mental health AI requires stronger safeguards than many general-purpose AI applications because users may interact with these systems during periods of vulnerability.
The major risks include hallucinations, inappropriate advice, privacy breaches, emotional dependency, bias, incorrect risk classification and failure to escalate emergencies.
| Risk | Why It Matters | Recommended Protection |
|---|---|---|
| Hallucinations | Incorrect clinical information | Grounded knowledge and human review |
| Crisis response | Potential harm during emergencies | Dedicated escalation protocols |
| Privacy | Mental health data is highly sensitive | Encryption and strict access controls |
| Bias | Unequal performance across populations | Subgroup validation |
| Dependency | Users may over-rely on AI | Clear boundaries and human referral |
| False reassurance | Risk may be missed | Conservative escalation thresholds |
Legacy Mental Health System Modernization
Existing mental health organizations do not need to replace their entire healthcare technology infrastructure to adopt AI.
A practical modernization strategy is to build an AI layer around existing electronic health records, scheduling platforms, patient portals and clinical workflows.
Legacy-to-AI Modernization
Existing EHR / Practice Management System
+
AI Integration Layer
+
Clinical Documentation
+
Patient Communication
+
Analytics & Monitoring
+
Human Clinical Oversight
The first projects should generally focus on high-volume, lower-risk processes. Documentation, intake, appointment automation, patient reminders and outcome tracking can create measurable value before an organization moves into more sensitive predictive or conversational applications.
Opportunity Matrix for Mental Health Startups
| Opportunity | Market Potential | Clinical Risk | Near-Term Potential |
|---|---|---|---|
| AI documentation | Very High | Low-Medium | Very High |
| AI intake | High | Medium | Very High |
| Patient monitoring | High | Medium-High | High |
| AI chatbot | Very High | High | High |
| Risk prediction | High | Very High | Research-led |
| Autonomous diagnosis | Potentially High | Very High | Limited |
Five-Stage AI Adoption Framework
Stage 1: Automate
Start with scheduling, reminders, intake forms, referral routing and administrative communication.
Stage 2: Assist
Add clinical documentation, session summaries and research assistance while keeping clinician approval mandatory.
Stage 3: Monitor
Introduce structured outcome tracking, symptom trends and patient engagement analytics.
Stage 4: Predict
Use validated machine-learning models for treatment response, deterioration signals or operational forecasting.
Stage 5: Personalize
Build adaptive AI systems that personalize education, monitoring and clinician-approved interventions.
Future Predictions: 2027–2030
Prediction 1: AI Documentation Will Become Normal
Ambient documentation is likely to become one of the most widely adopted healthcare AI capabilities because it solves a clear operational problem without requiring autonomous diagnosis.
Prediction 2: AI Will Become a Therapist Copilot
Instead of replacing therapists, AI will increasingly prepare patient summaries, identify changes in symptoms, organize treatment goals and assist with documentation.
Prediction 3: Multimodal Mental Health AI Will Expand
Future platforms will increasingly combine conversation, speech, questionnaires, behavioral data and wearable signals to create longitudinal patient profiles.
Prediction 4: AI Will Support Stepped-Care Models
AI may help route people toward different levels of support. Lower-risk patients could receive self-guided interventions, while concerning patterns trigger human assessment.
Prediction 5: Clinical Evidence Will Separate Serious Companies From Consumer Apps
As the market becomes crowded, healthcare buyers will increasingly demand randomized trials, external validation, safety evidence and measurable clinical outcomes.
Prediction 6: Crisis Safety Will Become a Core Product Feature
Mental health AI platforms will increasingly compete on their ability to identify risk and safely escalate users rather than simply generating empathetic responses.
Prediction 7: Personalized Therapy Support Will Grow
AI will increasingly adapt psychoeducation, reminders, exercises and monitoring according to individual patient progress while leaving treatment decisions to professionals.
Prediction 8: Mental Health AI Will Move Into Primary Care
Primary care will increasingly use AI-supported screening and monitoring because many patients encounter general healthcare providers before specialists.
Expert Recommendations
- Start with workflow problems. Choose processes where AI can save time without making autonomous clinical decisions.
- Use validated clinical instruments. AI should complement established assessment tools rather than inventing its own diagnostic standards.
- Keep a human in the loop. Clinicians should approve important clinical outputs and treatment decisions.
- Build crisis escalation separately. Do not expect a general-purpose LLM to manage emergencies by itself.
- Measure real outcomes. Track symptom scores, adherence, patient experience, safety events and clinically meaningful improvement.
- Validate across populations. Test performance across age groups, languages, cultures and socioeconomic settings.
- Protect mental health data. Use strict access control, encryption, data minimization and clear retention policies.
- Monitor AI after deployment. Performance can change when patient populations, workflows or underlying models change.
- Train clinicians. Staff should understand hallucinations, bias, privacy risks and appropriate AI use.
- Design for human connection. AI should increase the capacity of mental health professionals rather than remove the human relationship from care.
Original Research Asset: Mental Health AI Opportunity Map
| AI Capability | Clinical Value | Implementation Difficulty | 2027–2030 Outlook |
|---|---|---|---|
| Documentation AI | Very High | Medium | Mainstream |
| AI Intake | High | Medium | Mainstream |
| AI Monitoring | Very High | High | Strong Growth |
| Conversational AI | High | High | Strong Growth |
| Risk Prediction | Very High | Very High | Research / Regulated |
| Autonomous Therapy | Potentially High | Very High | Limited / Specialized |
Frequently Asked Questions
Can AI replace psychologists and psychotherapists?
No. Current evidence supports AI as a support technology rather than a replacement for qualified professionals. AI can assist with documentation, monitoring, education and structured interventions, while clinicians remain responsible for diagnosis, treatment and high-risk decisions.
Does AI actually improve depression and anxiety?
Research increasingly suggests that conversational AI and chatbot interventions can reduce depressive and anxiety symptoms. However, the average effects are generally modest, study populations vary and long-term evidence remains less developed.
Can AI diagnose depression from speech?
Research shows that machine-learning systems can identify speech patterns associated with depression with promising diagnostic performance. However, speech analysis should currently be treated as an additional assessment signal rather than an autonomous diagnosis.
Is generative AI safe for psychotherapy?
Generative AI can support mental health care when deployed within controlled clinical workflows, but unrestricted systems can produce incorrect or unsafe responses. Crisis escalation, privacy protection and professional oversight are essential.
What is the best first AI project for a mental health clinic?
AI documentation, intake automation, scheduling, patient reminders and outcome monitoring are strong starting points because they offer measurable operational value without immediately placing autonomous AI in control of clinical decisions.
What is the biggest future opportunity?
The biggest opportunity is likely to be an AI-enabled care platform that combines patient intake, documentation, monitoring, personalization, workflow automation and clinician decision support into one connected system.
Credible Research Sources
- WHO: Over a Billion People Living With Mental Health Conditions
- WHO: World Mental Health Today
- WHO: Mental Health Atlas 2024
- World Psychiatry: Evolution of AI Mental Health Chatbots From Rule-Based Systems to LLMs
- Generative AI Mental Health Chatbots: Systematic Review and Meta-Analysis
- Systematic Review and Meta-Analysis of Chatbots for Depression and Anxiety
- Randomized Clinical Trial of Conversational AI for Psychiatric Symptoms
- AI Conversational Agents for Young People’s Mental Health
- Deep Learning Speech Analysis for Depression Detection
- Traditional and Deep Learning Methods for Depression Detection From Speech
- Commercial AI Mental Health Chatbots: Systematic Review and Meta-Analysis
- AI Conversational Agents for Mental Health and Well-Being: Systematic Review and Meta-Analysis
- WHO: Responsible AI for Mental Health and Well-Being
- American Medical Association: Physician AI Adoption
- FDA: Artificial Intelligence-Enabled Medical Devices
AI Development Opportunities for Healthcare Organizations
Mental health organizations can approach AI as a complete technology modernization program rather than a single chatbot project.
The technology stack can include AI development, AI integration and deployment, workflow automation, machine learning, custom model development, data analytics, computer vision where appropriate and generative AI.
Potential implementation areas include AI development, AI integration, AI workflow automation, machine learning, custom AI model development, data analytics and AI insights and generative AI development.
Conclusion
Artificial intelligence is becoming a meaningful part of mental health and psychotherapy, but its role is more nuanced than the idea of an “AI therapist.”
The strongest evidence now shows that conversational AI can improve some depression, anxiety and well-being outcomes in controlled studies. At the same time, research shows that many newer LLM-based systems remain early in clinical validation, while commercial products can produce statistically significant improvements that are not always clinically large.
The biggest opportunity therefore lies in hybrid care. AI can collect and organize information, reduce documentation, monitor outcomes, personalize education, support structured interventions and identify signals that deserve clinical attention.
Clinicians should remain responsible for diagnosis, treatment decisions, therapeutic relationships and crisis intervention.
For healthcare startups, the opportunity is to build evidence-based AI systems around real clinical workflows. For established mental health organizations, the opportunity is to modernize legacy systems gradually and add AI where it can increase capacity without compromising safety.
The future of mental health AI will not be decided by which chatbot sounds the most human. It will be decided by which systems can demonstrate measurable clinical value, protect sensitive patient data, work reliably across diverse populations and safely connect artificial intelligence with human care.
Leave a Reply